What does this procedure involve?
A urethral diverticulum is a “pocket” or outpouching that forms next to your urethra (waterpipe). Because it connects to the urethra, this outpouching repeatedly fills with urine when you empty your bladder and causes symptoms. This procedure removes the diverticulum through a cut in your vagina.
What are the alternatives?
- No treatment – if your diverticulum causes no symptoms, sometimes it can be left alone and not treated
- Opening the diverticulum into the vagina – the diverticulum can be opened with a small incision into your vagina, and not removed; this is not usually as good as removing it
What happens on the day of the procedure?
You will be seen by the surgeon and the anaesthetist who will go through the plans for your operation with you.
We may provide you with a pair of TED stockings to wear, and give you an injection to thin your blood. These help to prevent blood clots from developing and passing into your lungs. Your medical team will decide whether you need to continue these after you go home.
Details of the procedure
- we normally carry out the procedure under a general anaesthetic (with you asleep) or a spinal anaesthetic (where you are awake but unable to feel anything below your waist)
- the surgeon will look inside your urethra and bladder using a telescope (cystoscope)
- we make a small incision inside your vagina
- we separate the diverticulum from your urethra and remove it; this leaves a small hole in your urethra which we repair using fine dissolvable stitches
- we usually reinforce the repaired area by positioning some of your body’s own tissue over your urethra; this might be some tissue from under your vaginal skin or fat from your labia (the hair-bearing vaginal lips)
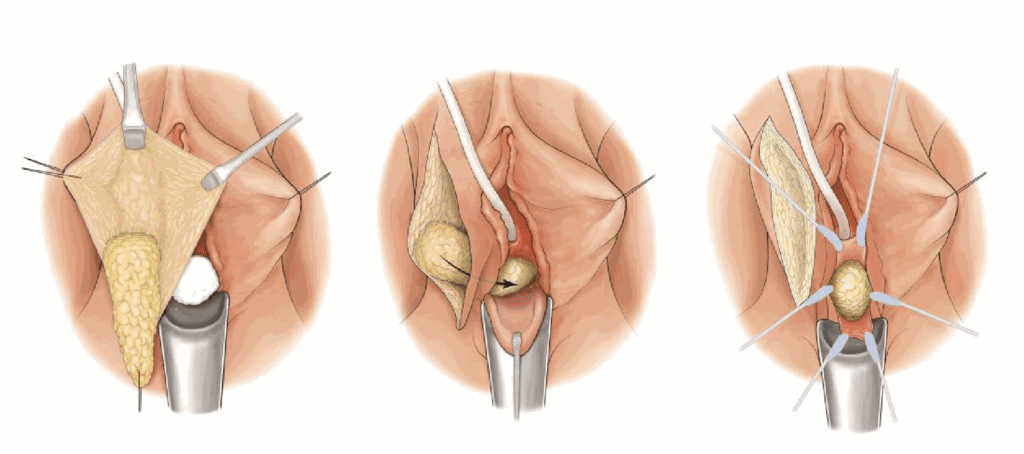
- if tissue from the labial lips is used, you will have a small cut over your labia. We sometimes leave a small drain in place; this is a small plastic tube that comes out of the skin and helps any blood drain out; it is usually removed a day or two after the operation
- we use dissolvable stitches in your vaginal skin (and in your labia, if needed) which disappear after two to three weeks
- we often place a small pack inside your vagina; this is usually removed the next day
- you will have a catheter inside your bladder through your urethra; this will stay in after you go home so that your urethra has had a chance to heal. Your surgeon will tell you when it will be removed
- sometimes, we put another catheter into your bladder through your abdomen (tummy) as well; this is called a suprapubic catheter
You may experience some bleeding from your vagina over the first few days, but this usually stops quickly.
Your catheter needs to stay in for at least two weeks but you will be able to go home with the catheter. When it is removed, you may get some discomfort passing urine at first.
Are there any after-effects?
The possible after-effects and your risk of getting them are shown below. Some are self-limiting or reversible, but others are not. We have not listed very rare after-effects (occurring in less than 1 in 250 patients) individually. The impact of these after-effects can vary a lot from patient to patient; you should ask your surgeon’s advice about the risks and their impact on you as an individual:
| After-effect | Risk |
|---|---|
| Mild vaginal bleeding (for the first two days), bruising or blood clot under your skin |
 Almost all patients |
| Temporary pain in your incisions requiring simple painkillers such as aspirin, paracetamol or ibuprofen |
Almost all patients |
| Chronic (long-term) pain in your pelvic area |
 Between 1 in 10 & 1 in 20 patients (5–10%) |
| Stress incontinence (leakage of urine when you cough, sneeze or exercise) |
Between 1 in 10 & 1 in 20 patients (5–10%) |
| Wound infection |
Between 1 in 20 & 1 in 50 patients (2–5%) |
| Recurrence of the diverticulum (i.e. the problem comes back again) |
Between 1 in 20 & 1 in 50 patients (2–5%) |
| Difficulty passing urine due to scarring & narrowing of your urethra |
Between 1 in 20 & 1 in 50 patients (2–5%) |
| Change in the shape or appearance of your labia (vaginal lips) |
 Between 1 in 50 & 1 in 250 patients (less than 2%) |
| Fistula (a connection between the urethra and the vaginal skin with possible leakage of urine) |
Less than 1 in 50 patients (less than 2%) |
| Severe bleeding requiring a further procedure |
Between 1 in 50 & 1 in 250 patients |
| Anaesthetic or cardiovascular problems possibly requiring intensive care (including chest infection, pulmonary embolus, stroke, deep vein thrombosis, heart attack and death) |
Between 1 in 50 & 1 in 250 patients (your anaesthetist can estimate your individual risk) |
What is my risk of a hospital-acquired infection?
Your risk of getting an infection in hospital is between 4 & 6%; this includes getting MRSA or a Clostridium difficile bowel infection. Individual hospitals may have different rates, and the medical staff can tell you the risk for your hospital. You have a higher risk if you have had:
- long-term drainage tubes (e.g. catheters);
- bladder removal;
- long hospital stays; or
- multiple hospital admissions.
What can I expect when I get home?
- you will be given a copy of your discharge summary and a copy will also be sent to your GP
- you will be discharged with a catheter in your bladder; we will show you how to manage it at home and arrange for it to be removed at a suitable time
- you may get pain in your vagina for a few weeks afterwards; simple painkillers usually help
- for the first four weeks, you should avoid any strenuous activity or heavy lifting
- after four weeks, you may return to everyday activities; if you do a very heavy job or partake in strenuous exercises such as running or gym work, you should wait for longer and start gradually
- you will need at least three weeks off work; you may need longer if you have a strenuous job (your surgical team will be able to advise you about this)
- you should avoid sexual intercourse for six weeks after the procedure
General information about surgical procedures
Before your procedure
Please tell a member of the medical team if you have:
- an implanted foreign body (stent, joint replacement, pacemaker, heart valve, blood vessel graft);
- a regular prescription for a blood thinning agent (e.g. warfarin, aspirin, clopidogrel, rivaroxaban, dabigatran);
- a present or previous MRSA infection; or
- a high risk of variant-CJD (e.g. if you have had a corneal transplant, a neurosurgical dural transplant or human growth hormone treatment).
Questions you may wish to ask
If you wish to learn more about what will happen, you can find a list of suggested questions called “Having An Operation” on the website of the Royal College of Surgeons of England. You may also wish to ask your surgeon for his/her personal results and experience with this procedure.
Before you go home
We will tell you how the procedure went and you should:
- make sure you understand what has been done;
- ask the surgeon if everything went as planned;
- let the staff know if you have any discomfort;
- ask what you can (and cannot) do at home;
- make sure you know what happens next; and
- ask when you can return to normal activities.
We will give you advice about what to look out for when you get home. Your surgeon or nurse will also give you details of who to contact, and how to contact them, in the event of problems.
Smoking and surgery
Ideally, we would prefer you to stop smoking before any procedure. Smoking can worsen some urological conditions and makes complications more likely after surgery. For advice on stopping, you can:
- contact your GP;
- access your local NHS Smoking Help Online; or
- ring the free NHS Smoking Helpline on 0300 1044.
Driving after surgery
It is your responsibility to make sure you are fit to drive after any surgical procedure. You only need to contact the DVLA if your ability to drive is likely to be affected for more than three months. If it is, you should check with your insurance company before driving again. You should not drive until you can move safely around the car and perform emergency braking without any pain. If you experience any pain on braking, you should not drive until it settles.