What does this procedure involve?
Removal of one kidney through an incision in your abdomen or loin.
What are the alternatives?
- Observation alone – leaving your kidney in place and observing it carefully for any signs of progressive disease
- Laparoscopic simple nephrectomy – removing the kidney using a telescopic (keyhole) technique; this can be performed using robotic assistance
- Ureteric stent insertion – for a kidney which is blocked and functioning poorly, it may be possible to put a drainage stent into the ureter; this can be changed every six months
What happens on the day of the procedure?
Your urologist (or a member of their team) will briefly review your history and medications, and will discuss the surgery again with you to confirm your consent.
An anaesthetist will see you to discuss the options of a general anaesthetic or spinal anaesthetic. The anaesthetist will also discuss pain relief after the procedure with you.
We may provide you with a pair of TED stockings to wear, and we may give you a heparin injection to thin your blood. These help to prevent blood clots from developing and passing into your lungs. Your medical team will decide whether you need to continue these after you go home.
Details of the procedure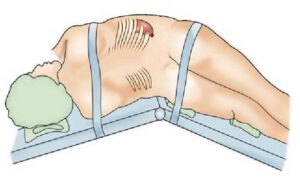
- We normally carry out the procedure under a general anaesthetic
- We may give you an injection of antibiotics before the procedure, after you have been checked for any allergies
- We remove your kidney through an incision in your loin (pictured); occasionally, we may need to extend the incision into your abdominal area or chest
- We close the wound with absorbable stitches (which normally disappear within two to three weeks) or staples, and we inject local anaesthetic into the wound for pain relief
- We put a catheter in your bladder to monitor your urine output; this is removed as soon as you are mobile
- We usually put a drain down to the area where the tumour was removed, to prevent fluid accumulation; this is removed when it stops draining
- We may put a tube through your nose into your stomach (nasogastric tube) to prevent “bloating” of your abdomen (tummy), especially if the procedure proves particularly difficult
- You can expect to be in hospital for seven days
Following major abdominal surgery, some urology units have introduced Enhanced Recovery Pathways. These actually start before you are admitted to hospital. After your surgery, they are designed to speed your recovery, shorten your time in hospital and reduce your risk of re-admission.
We will encourage you to get up and about as soon as possible. This reduces the risk of blood clots in your legs and helps your bowel to start working again. You will sit out in a chair shortly after the procedure and be shown deep breathing/leg exercises. We will remove your nasogastric tube as soon as your bowel starts functioning normally and we will encourage you to start drinking and eating as soon as possible.
Are there any after-effects?
The possible after-effects and your risk of getting them are shown below. Some are self-limiting or reversible, but others are not. We have not listed very rare after-effects (occurring in less than 1 in 250 patients) individually. The impact of these after-effects can vary a lot from patient to patient; you should ask your surgeon’s advice about the risks and their impact on you as an individual:
| After-effect | Risk |
|---|---|
| Bulging of your abdominal wall below the wound due to damage to the nerves supplying the muscles |
 Almost all patients |
| Bleeding, infection or pain at the incision site requiring further treatment |
 Between 1 in 2 & 1 in 10 patients |
| Bleeding requiring transfusion or further surgery |
 Between 1 in 10 & 1 in 50 patients |
| Entry into your lung cavity requiring insertion of a temporary drainage tube |
Between 1 in 10 & 1 in 50 patients |
| Tingling or numbness below the wound due to nerves being trapped in the scar |
Between 1 in 10 & 1 in 50 patients |
| Hernia in the loin incision requiring further treatment |
 Between 1 in 50 & 1 in 250 patients |
| Anaesthetic or cardiovascular problems possibly requiring intensive care (including chest infection, pulmonary embolus, stroke, deep vein thrombosis, heart attack and death) |
Between 1 in 50 & 1 in 250 patients (your anaesthetist can estimate your individual risk) |
| Involvement or injury to nearby local structures (blood vessels, spleen, liver, lung, pancreas & bowel) requiring more extensive surgery |
Between 1 in 50 & 1 in 250 patients |
What is my risk of a hospital-acquired infection?
Your risk of getting an infection in hospital is between 4 & 6%; this includes getting MRSA or a Clostridium difficile bowel infection. This figure is higher if you are in a “high-risk” group of patients such as patients who have had:
- Long-term drainage tubes (e.g. catheters);
- Bladder removal;
- Long hospital stays; or
- Multiple hospital admissions.
What can I expect when I get home?
- You will get some twinges of discomfort in your incisions which may go on for several weeks; this can be controlled by simple painkillers such as paracetamol
- We normally arrange to remove any staples or stitches in your incision after seven to 10 days
- Most people can return to work after two to three weeks
- You should have recovered completely after four to six weeks
- You will be given advice about your recovery at home
- You will be given a copy of your discharge summary and a copy will also be sent to your GP
- Any antibiotics or other tablets you may need will be arranged & dispensed from the hospital pharmacy
When your kidney has been removed through a loin incision, the abdominal wall below your scar will bulge; this is not a hernia but is caused by nerve damage. It can be helped by strengthening up the muscles of your abdominal wall. We can arrange for you to see a physiotherapist who will show you exercises to strengthen these muscles.
General information about surgical procedures
Before your procedure
Please tell a member of the medical team if you have:
- An implanted foreign body (stent, joint replacement, pacemaker, heart valve, blood vessel graft);
- A regular prescription for a blood thinning agent (e.g. warfarin, aspirin, clopidogrel, rivaroxaban, dabigatran);
- A present or previous MRSA infection; or
- A high risk of variant-CJD (e.g. if you have had a corneal transplant, a neurosurgical dural transplant or human growth hormone treatment).
Questions you may wish to ask
If you wish to learn more about what will happen, you can find a list of suggested questions called “Having An Operation” on the website of the Royal College of Surgeons of England. You may also wish to ask your surgeon for his/her personal results and experience with this procedure.
For several years, BAUS has collected data from urologists undertaking this surgery. You can view these data, by unit and by Consultant, in the Surgical Outcomes Audit section of the BAUS website.
Before you go home
We will tell you how the procedure went and you should:
- Make sure you understand what has been done;
- Ask the surgeon if everything went as planned;
- Let the staff know if you have any discomfort;
- Ask what you can (and cannot) do at home;
- Make sure you know what happens next; and
- Ask when you can return to normal activities.
We will give you advice about what to look out for when you get home. Your surgeon or nurse will also give you details of who to contact, and how to contact them, in the event of problems.
Smoking and surgery
Ideally, we would prefer you to stop smoking before any procedure. Smoking can worsen some urological conditions and makes complications more likely after surgery. For advice on stopping, you can:
- Contact your GP;
- Access your local NHS Smoking Help Online; or
- Ring the free NHS Smoking Helpline on 0800 169 0 169.
Driving after surgery
It is your responsibility to make sure you are fit to drive after any surgical procedure. You only need to contact the DVLA if your ability to drive is likely to be affected for more than three months. If it is, you should check with your insurance company before driving again.