What does this procedure involve?
Removal of the obstructing, central portion of your prostate gland through an abdominal incision; it is only used when the prostate gland is too big or not suitable for removal using a telescope.
Our aims in men with a large obstructing prostate gland are:
- To remove the obstructing lobes of the prostate
- To allow you to pass urine with a stronger flow
- To reduce as many of your urinary symptoms as possible
- To preserve your continence
- To preserve the erection nerves to your penis
What are the alternatives for large, obstructing prostates?
- Drugs – tablets that shrink or relax the prostate to help you pass urine; most patients try these first before surgery
- Long-term catheter – to drain your bladder permanently (this needs a change of catheter every eight to 12 weeks)
- Holmium laser enucleation of the prostate (HoLEP) – using a laser fibre passed along a telescope through your urethra (waterpipe)
- Transurethral resection of the prostate (TURP) – coring out your prostate gland to improve the flow of urine. TURP is the most performed prostate procedure and most men get good relief of their symptoms. Large prostates, however, are not always suitable for TURP
- Green light laser prostatectomy (GLLP) – creating a hole in the central part of the prostate using a laser that melts tissue away by vaporising it
- Prostate artery embolisation – blocking the arteries to the prostate under local anaesthetic so that the prostate shrinks; normally performed by a highly-skilled “interventional” radiologist (not a urologist)
Deciding which treatment to have is not something you will do alone; it may depend on the level of expertise available at your hospital. If you need further information, please contact your specialist nurse, surgical care practitioner or urologist.
What happens on the day of the procedure?
Your urologist (or a member of their team) will briefly review your history and medications, and will discuss the surgery again with you to confirm your consent.
An anaesthetist will see you to discuss the options of a general anaesthetic or spinal anaesthetic. The anaesthetist will also discuss pain relief after the procedure with you.
We may provide you with a pair of TED stockings to wear, and we may give you a heparin injection to thin your blood. These help to prevent blood clots from developing and passing into your lungs. Your medical team will decide whether you need to continue these after you go home.
Details of the procedure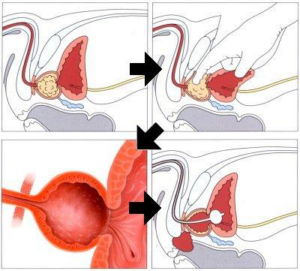
- We normally perform the procedure under a general anaesthetic (with you asleep) but we sometimes use a spinal anaesthetic (where you are unable to feel anything from the waist down)
- All methods reduce the level of pain afterwards
- We will give you an injection of antibiotics before the procedure, after carefully checking for any allergies
- We use a cystoscope (telescope) to look inside your bladder and to assess your prostate
- We make a single incision (cut) in your abdomen (tummy), either vertically or horizontally
- We cut into the outer shell of your prostate gland and remove the central part
- We normally insert a bladder catheter; this stays in for about a week to allow the prostate capsule heal
- We put in a drain to stop any fluid collecting around your prostate; this is normally removed after two to four days
- We use absorbable stitches in your skin which do not require removal, and normally disappear within two to three weeks
What happens immediately after the procedure?
You should be told how the procedure went and you should:
- Ask the surgeon if it went as planned
- Let the medical staff know if you are in any discomfort
- Ask what you can and cannot do
- Feel free to ask any questions or discuss any concerns with the ward staff and members of the surgical team
- Make sure that you are clear about what has been done and what happens next
You will have some bleeding from the prostate area after the operation but the urine usually clears after 48 hours. Some patients may lose more blood for longer. If blood loss is large, you may require a blood transfusion to prevent you from becoming anaemic. You will be able to eat and drink the morning after the operation; this may be allowed earlier after a spinal anaesthetic.
Your drain is usually removed after two to four days, and the catheter after four to six days, after which urine can be passed in the normal way. At first, you may get pain when passing urine and it may come more frequently than normal. Any discomfort can be relieved by tablets or injections and the frequent passage usually improves within a few days.
It is not unusual for your urine to turn bloody again after your catheter is removed; some patients cannot pass urine at all after the operation. If cannot pass urine, we will pass another catheter to let your bladder recover, before trying again without the catheter.
The average hospital stay is seven days for a routine admission and 10 days following emergency admission.
Are there any after-effects?
The possible after-effects and your risk of getting them are shown below. Some are self-limiting or reversible, but others are not. We have not listed very rare after-effects (occurring in less than 1 in 250 patients) individually. The impact of these after-effects can vary a lot from patient to patient; you should ask your surgeon’s advice about the risks and their impact on you as an individual:
| After-effect | Risk |
|---|---|
| No semen is produced during orgasm, effectively making you infertile |
 All patients |
| Persisting symptoms of urgency, frequency by day & getting up at night to pass urine |
 Almost all patients |
| Inability to pass urine after the catheter is removed needing intermittent catheterisation or a permanent catheter |
 Between 1 in 20 & 1 in 33 patients (3 to 5%) |
| Erectile dysfunction (impotence) if nerve damage is unavoidable, together with some shortening of your penis |
Between 1 in 10 & 1 in 50 patients |
| Because the outer layer of the prostate remains intact, you may develop prostate cancer in the future; you should discuss PSA testing with your surgeon and GP |
Between 1 in 10 & 1 in 50 patients |
| Pathology tests may show unexpected cancer in the prostate tissue removed requiring observation, investigations &/or possible further treatment |
Between 1 in 10 & 1 in 50 patients |
| Bleeding requiring transfusion or further surgery |
Between 1 in 10 & 1 in 50 patients |
| Scarring of the bladder neck or urethra requiring stretching or further treatment |
Between 1 in 10 & 1 in 50 patients |
| Pain, infection or hernia in the incision requiring further treatment |
Between 1 in 10 & 1 in 50 patients |
| Anaesthetic or cardiovascular problems possibly requiring intensive care admission (including chest infection, pulmonary embolus, stroke, deep vein thrombosis, compartment syndrome, heart attack) |
 Between 1 in 50 & 1 in 250 patients (your anaesthetist can estimate your individual risk) |
| Urinary incontinence which may be temporary and require pads; this may need further surgery if it lasts for more than a year (with an artificial urinary sphincter or a synthetic male sling) |
Between 1 in 50 & 1 in 250 patients |
What is my risk of a hospital-acquired infection?
Your risk of getting an infection in hospital is between 4 & 6%; this includes getting MRSA or a Clostridium difficile bowel infection. This figure is higher if you are in a “high-risk” group of patients such as patients who have had:
- Long-term drainage tubes (e.g. catheters)
- Long hospital stays
- Multiple hospital admissions
What can I expect when I get home?
- You will get some swelling and bruising of the incisions which may last several days
- It may be several days before you have your bowels open
- You may be discharged with a catheter in your bladder
- If you do have a catheter, we will show you how to manage it at home
- You will be given advice about your recovery at home
- You will be given a copy of your discharge summary and a copy will also be sent to your GP
- Any antibiotics or other tablets you may need will be arranged & dispensed from the hospital pharmacy
- A follow-up appointment will be made for you to have your dressings and your catheter removed
- If you develop a fever, severe pain when passing urine, you cannot pass urine or any bleeding gets worse, you should contact your GP immediately
- If you develop a temperature, increased redness, throbbing or drainage at the site of the operation, please contact your GP
- 20% of men (1 in 5) experience further bleeding 10 to 14 days after getting home; this is due to scabs separating from the cavity of the prostate. If you increase your fluid intake, the bleeding should stop quickly; if it does not, you should contact your GP who will prescribe some antibiotics for you. Some men with severe bleeding, passage of clots or sudden difficulty in passing urine, may need to be readmitted to hospital
Removal of your prostate should not adversely affect your sex life provided you get normal erections. You may have sex as soon as you are comfortable, usually after three to four weeks.
You should start pelvic floor exercises as soon as possible after the operation because they improve your control when you get home. If you need any specific information on these exercises, please contact the ward staff or the specialist nurses. The symptoms of an overactive bladder may take three months to resolve whereas the flow is improved immediately.
It will be 14 to 21 days before the biopsy results on the prostate tissue removed are available. All biopsies are discussed in detail at a multi-disciplinary meeting before any further treatment decisions are made. You and your GP will be informed of the results after this discussion.
It is not always necessary for patients to be reviewed in outpatients; you will be given an appropriate follow-up plan when you leave hospital.
General information about surgical procedures
Before your procedure
Please tell a member of the medical team if you have:
- An implanted foreign body (stent, joint replacement, pacemaker, heart valve, blood vessel graft)
- A regular prescription for a blood thinning agent (e.g. warfarin, aspirin, clopidogrel, rivaroxaban, dabigatran)
- A present or previous MRSA infection
- A high risk of variant-CJD (e.g. if you have had a corneal transplant, a neurosurgical dural transplant or human growth hormone treatment)
Questions you may wish to ask
If you wish to learn more about what will happen, you can find a list of suggested questions called “Having An Operation” on the website of the Royal College of Surgeons of England. You may also wish to ask your surgeon for his/her personal results and experience with this procedure.
Before you go home
We will tell you how the procedure went and you should:
- Make sure you understand what has been done
- Ask the surgeon if everything went as planned
- Let the staff know if you have any discomfort
- Ask what you can (and cannot) do at home
- Make sure you know what happens next
- Ask when you can return to normal activities
We will give you advice about what to look out for when you get home. Your surgeon or nurse will also give you details of who to contact, and how to contact them, in the event of problems.
Smoking and surgery
Ideally, we would prefer you to stop smoking before any procedure. Smoking can worsen some urological conditions and makes complications more likely after surgery. For advice on stopping, you can:
- Contact your GP
- Access your local NHS Smoking Help Online
- Ring the free NHS Smoking Helpline on 0300 123 1044
Driving after surgery
It is your responsibility to make sure you are fit to drive after any surgical procedure. You only need to contact the DVLA if your ability to drive is likely to be affected for more than three months. If it is, you should check with your insurance company before driving again.