What does this procedure involve?
Bladder neck incision involves cutting through the neck of your bladder to allow you to pass urine more easily and with a better stream.
What are the alternatives?
- Observation – no treatment, but monitoring of any change in your symptoms; symptoms can improve over time without any treatment
- Drugs to improve urine flow – by relaxing the thickened muscle at the neck of your bladder e.g. tamsulosin, doxazosin, terazosin
- Bladder neck incision using laser energy – some surgeons prefer to cut the bladder neck with a laser rather than with an electric “spike”
- Transurethral prostatectomy (TURP) – we may choose to do this instead of, or in addition to, a BNI if it is felt necessary to relieve your symptoms
What happens on the day of the procedure?
Your urologist (or a member of their team) will briefly review your history and medications, and will discuss the surgery again with you to confirm your consent.
An anaesthetist will see you to discuss the options of a general anaesthetic or spinal anaesthetic. The anaesthetist will also discuss pain relief after the procedure with you.
We may provide you with a pair of TED stockings to wear, and we may give you a heparin injection to thin your blood. These help to prevent blood clots from developing and passing into your lungs. Your medical team will decide whether you need to continue these after you go home.
Details of the procedure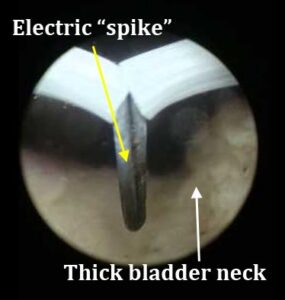
- We normally use either a general anaesthetic (where you are asleep) or a spinal anaesthetic (where you are unable to feel anything from your waist down)
- We usually give you an injection of antibiotics before the procedure, after you have been checked for any allergies
- We put a telescope into your bladder through the urethra (water pipe) to check that there are no other problems within your bladder
- We use an electric “spike” to cut through the thickened muscle at the neck of the bladder
- Occasionally, we may feel it necessary to remove some prostate tissue as well, to make sure that the urinary channel remains clear and open
- We put a catheter into your bladder at the end of the procedure
- We normally use bladder irrigation through the catheter to flush out any clots or bleeding
- On average, the procedure takes 20 to 30 minutes to complete
- You can expect to stay in hospital for one to two nights after the surgery
We usually remove your bladder catheter after one night. You may find it painful to pass urine at first and it may come more frequently than normal. Tablets or injections can help with this, but it usually improves within a few days.
Your urine may turn bloody for 24 to 48 hours after removal of your catheter and some patients cannot pass urine at this stage. If this happens, we put another catheter in, before removing it again 48 hours later.
Further information and a short video of bladder neck incision are available on the BAUS website.
Are there any after-effects?
The possible after-effects and your risk of getting them are shown below. Some are self-limiting or reversible, but others are not. We have not listed very rare after-effects (occurring in less than 1 in 250 patients) individually. The impact of these after-effects can vary a lot from patient to patient; you should ask your surgeon’s advice about the risks and their impact on you as an individual:
| After-effect | Risk |
|---|---|
| Temporary mild burning, bleeding and frequent urination |
 Almost all patients |
| Urinary tract infection requiring treatment with antibiotics |
 Between 1 in 2 & 1 in 10 patients |
| No semen is produced because it passes back into your bladder on ejaculation (retrograde ejaculation) |
Between 1 in 2 & 1 in 10 patients |
| Failure to relieve your symptoms completely |
Between 1 in 50 and 1 in 100 |
| Anaesthetic or cardiovascular problems possibly requiring intensive care (including chest infection, pulmonary embolus, stroke, deep vein thrombosis, heart attack and death) |
 Between 1 in 50 & 1 in 250 patients (your anaesthetist can estimate your individual risk) |
| Injury to the urethra causing delayed scar formation |
Between 1 in 100 & 1 in 250 patients |
What is my risk of a hospital-acquired infection?
Your risk of getting an infection in hospital is approximately 8 in 100 (8%); this includes getting MRSA or a Clostridium difficile bowel infection. This figure is higher if you are in a “high-risk” group of patients such as patients who have had:
- Long-term drainage tubes (e.g. catheters)
- Long hospital stays
- Multiple hospital admissions
What can I expect when I get home?
- You will be given advice about your recovery at home
- You will be given a copy of your discharge summary and a copy will also be sent to your GP
- Any antibiotics or other tablets you may need will be arranged & dispensed from the hospital pharmacy
- You should drink twice as much fluid as you would normally for the first 24 to 48 hours, to flush your system through and reduce the risk of infection
- You may return to work when you are comfortable enough and when your GP is satisfied with your progress
- One patient in five (20%) gets some bleeding 10 to 14 days after getting home, due to scabs separating from the cavity of the prostate. If this happens, you should increase your drinking
- If it does not settle, you should contact your GP who will prescribe antibiotics for you
- If you have a fever, severe pain on passing urine, worsening bleeding, passing blood clots or sudden difficulty passing urine, you should contact your GP immediately; this may need re-admission as an emergency
General information about surgical procedures
Before your procedure
Please tell a member of the medical team if you have:
- An implanted foreign body (stent, joint replacement, pacemaker, heart valve, blood vessel graft)
- A regular prescription for a blood thinning agent (e.g. warfarin, aspirin, clopidogrel, rivaroxaban, dabigatran)
- A present or previous MRSA infection
- A high risk of variant-CJD (e.g. if you have had a corneal transplant, a neurosurgical dural transplant or human growth hormone treatment)
Questions you may wish to ask
If you wish to learn more about what will happen, you can find a list of suggested questions called “Having An Operation” on the website of the Royal College of Surgeons of England. You may also wish to ask your surgeon for his/her personal results and experience with this procedure.
Before you go home
We will tell you how the procedure went and you should:
- Make sure you understand what has been done
- Ask the surgeon if everything went as planned
- Let the staff know if you have any discomfort
- Ask what you can (and cannot) do at home
- Make sure you know what happens next
- Ask when you can return to normal activities
We will give you advice about what to look out for when you get home. Your surgeon or nurse will also give you details of who to contact, and how to contact them, in the event of problems.
Smoking and surgery
Ideally, we would prefer you to stop smoking before any procedure. Smoking can worsen some urological conditions and makes complications more likely after surgery. For advice on stopping, you can:
- Contact your GP
- Access your local NHS Smoking Help Online
- Ring the free NHS Smoking Helpline on 0300 123 1044
Driving after surgery
It is your responsibility to make sure you are fit to drive after any surgical procedure. You only need to contact the DVLA if your ability to drive is likely to be affected for more than three months. If it is, you should check with your insurance company before driving again.